


Cymbalta (duloxetine) and Prozac (fluoxetine) are both antidepressants, but Cymbalta is an SNRI and Prozac is an SSRI.
- Mechanism: Cymbalta raises both serotonin and norepinephrine. Prozac raises mainly serotonin.
- Uses: Cymbalta is also approved for nerve pain, fibromyalgia and chronic musculoskeletal pain. Prozac covers OCD, bulimia and panic disorder.
- How long they last: Cymbalta leaves the body within a few days (half-life about 12 hours). Prozac lingers for weeks (half-life 4 to 6 days, plus up to 16 days for its active metabolite). That shapes everything from missed doses to withdrawal to switching.
- Together: taking them at the same time is generally avoided. Fluoxetine blocks the enzyme that clears duloxetine, raising its levels, and two serotonin-boosting drugs together increase the risk of serotonin syndrome.
This is general information, not medical advice. Antidepressants should only be started, stopped, combined or switched under your prescriber’s direction.
Cymbalta vs Prozac at a glance
| Cymbalta (duloxetine) | Prozac (fluoxetine) | |
|---|---|---|
| Class | SNRI (serotonin-norepinephrine reuptake inhibitor) | SSRI (selective serotonin reuptake inhibitor) |
| Approved for | Depression (adults); generalized anxiety disorder (age 7+); diabetic nerve pain; fibromyalgia (age 13+); chronic musculoskeletal pain such as back pain and osteoarthritis | Depression (age 8+); OCD (age 7+); bulimia nervosa; panic disorder; with olanzapine, bipolar depression and treatment-resistant depression |
| Usual dose | 60 mg once daily (range 30 to 120 mg) | 20 to 60 mg once daily (up to 80 mg) |
| Half-life | About 12 hours | 4 to 6 days, plus 4 to 16 days for norfluoxetine |
| Withdrawal risk if stopped suddenly | High | Low |
| Notable extra risks | Raised blood pressure; liver injury (avoid with heavy drinking or liver disease) | Many drug interactions (strong CYP2D6 inhibitor) |
| Forms | Delayed-release capsules (swallow whole) | Capsules, tablets, liquid, weekly capsule |
| Generic | Yes | Yes |
How they work
Prozac blocks the serotonin transporter, so more serotonin stays active between nerve cells. It also mildly blocks a serotonin receptor (5-HT2C), which may explain why it can feel energizing for some people.
Cymbalta blocks reuptake of both serotonin and norepinephrine. Norepinephrine matters for pain: nerve pathways running from the brain down the spinal cord use serotonin and norepinephrine to turn down pain signals. Strengthening both is thought to be why SNRIs relieve some chronic pain conditions, while SSRIs like Prozac have weaker pain effects. The norepinephrine action also explains Cymbalta’s tendency to raise blood pressure and heart rate slightly, and to cause sweating and urinary hesitancy.
Which works better?
For depression, they’re broadly comparable. In the 2018 Lancet network meta-analysis of 21 antidepressants (Cipriani and colleagues), both duloxetine and fluoxetine were more effective than placebo. Neither stood far apart from the pack, and the analysis found antidepressants differed more in how well people tolerated them than in raw effect. Choosing between these two usually comes down to:
- Pain alongside depression or anxiety: Cymbalta has approvals and trial evidence for diabetic nerve pain, fibromyalgia, chronic low back pain and knee osteoarthritis pain. Prozac doesn’t.
- OCD, bulimia or panic disorder: Prozac is approved for these. Cymbalta isn’t.
- Children and teens: Prozac is approved for depression from age 8 and OCD from age 7. Cymbalta is approved for anxiety from age 7 and fibromyalgia from age 13, but not for depression in young people.
- Tolerability and practical issues such as withdrawal risk, blood pressure, liver concerns and interactions.
Half-life: the biggest practical difference
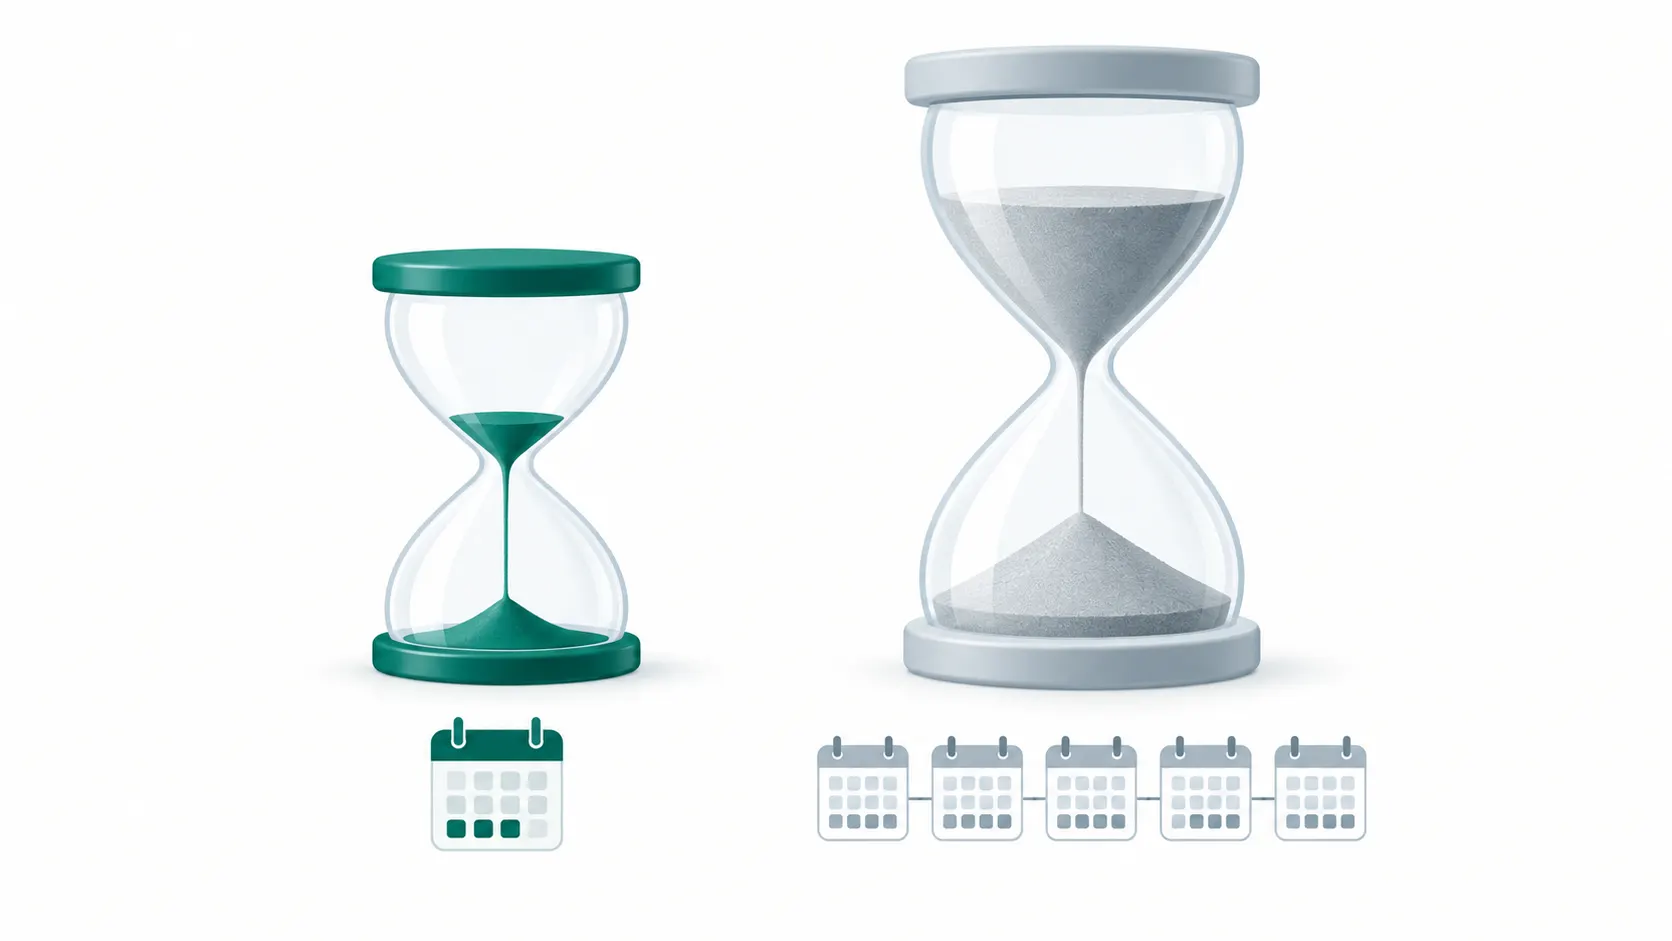
Duloxetine’s half-life is about 12 hours, so it’s mostly gone within 2 to 3 days of stopping. Fluoxetine’s half-life is 4 to 6 days after regular use, and its active metabolite norfluoxetine lasts 4 to 16 days. Traces remain for weeks. In daily life this means:
- Missed doses: forgetting a Cymbalta dose can bring dizziness or “brain zaps” within a day or two. Missing a Prozac dose usually goes unnoticed.
- Stopping: Cymbalta has one of the highest rates of discontinuation symptoms among antidepressants, and needs a slow taper. Prozac effectively tapers itself, and is sometimes used as a bridge to help people come off shorter-acting antidepressants.
- Side effects after stopping: if Prozac causes a problem, it takes weeks to clear completely. Cymbalta clears within days.
- Switching to an MAOI: you must wait at least 5 weeks after stopping Prozac, but only 5 days after stopping Cymbalta.
Can you take Cymbalta and Prozac together?
This is the most common question people ask about these two drugs, and the answer is: generally no, except briefly during a supervised switch. Three reasons:
- Serotonin syndrome: both raise serotonin. Combining them increases the risk of serotonin syndrome, which can range from shivering, sweating, diarrhea and agitation to high fever, muscle rigidity and seizures.
- Raised duloxetine levels: fluoxetine is a potent inhibitor of CYP2D6, one of the two liver enzymes that clear duloxetine. The Cymbalta label reports that paroxetine (a similar inhibitor) raised duloxetine levels by about 60%, and names fluoxetine as expected to do the same. Higher duloxetine levels mean more nausea, blood pressure rise, sweating and serotonin load.
- No proven extra benefit: there’s no good evidence that an SSRI plus an SNRI works better than an adequate dose of one. When a single antidepressant isn’t enough, guideline options are usually raising the dose, switching, or adding a drug from a different class (such as bupropion, mirtazapine, aripiprazole or lithium), not stacking two serotonin reuptake inhibitors.
Because Prozac lingers, it’s effectively “taken together” with Cymbalta for several weeks after a switch from Prozac to Cymbalta. That’s why prescribers usually start Cymbalta at a low dose (often 20 to 30 mg) after stopping fluoxetine and raise it cautiously.
Switching between Cymbalta and Prozac
- Prozac to Cymbalta: stop fluoxetine (often without a long taper, given its long half-life), then start duloxetine at a low dose a few days to a week later, increasing slowly while fluoxetine is still clearing. Watch for serotonin symptoms.
- Cymbalta to Prozac: duloxetine withdrawal is the main issue. A common approach is to taper duloxetine over a few weeks while starting fluoxetine at 10 to 20 mg. Fluoxetine’s long action can cushion duloxetine withdrawal. Some prescribers deliberately use this “fluoxetine bridge” to help people who struggle to come off Cymbalta.
Never work out a switch on your own. The timing depends on your doses, how long you’ve been taking each drug, and your other medicines.
Dosing compared
| Use | Cymbalta | Prozac |
|---|---|---|
| Depression (adults) | 40 to 60 mg/day; often 30 mg for the first week | Start 20 mg in the morning; up to 80 mg |
| Anxiety / panic | GAD: 60 mg (30 mg start in older adults and children 7+); up to 120 mg | Panic disorder: start 10 mg, usual 20 mg, up to 60 mg |
| Pain conditions | 60 mg once daily (start 30 mg); higher doses add side effects without clear extra pain relief | Not approved |
| OCD | Not approved | 20 to 60 mg (up to 80 mg) |
| Bulimia | Not approved | 60 mg each morning |
| How to take | Swallow capsule whole; don’t open, crush or chew. With or without food | Usually morning, because it can disturb sleep. With or without food |
Side effects compared
| Side effect | Cymbalta | Prozac |
|---|---|---|
| Nausea | Very common early on (about 1 in 4); usually settles | Common early on |
| Dry mouth, constipation, sweating | Common | Less common |
| Insomnia or feeling activated | Possible | Common; take in the morning |
| Sleepiness | Common | Less common |
| Sexual side effects | Common | Common |
| Blood pressure | Small average rise; check periodically | Little effect |
| Urinary hesitancy | Possible, especially in men with an enlarged prostate | Uncommon |
| Weight | Small changes; some gain with long-term use | Early weight loss sometimes, then neutral |
| Withdrawal on stopping | Frequent and can be severe | Uncommon and mild |
Cymbalta’s liver and alcohol warning
Duloxetine can rarely cause liver injury, including hepatitis and jaundice. The label advises against using it in people with substantial alcohol use or chronic liver disease, and lists alcohol use with duloxetine as linked to severe liver injury. Prozac has no equivalent liver warning, though heavy drinking is unwise with any antidepressant. If you drink regularly, tell your prescriber before starting Cymbalta. Our alcohol and medication interaction checker covers both drugs.
Warnings shared by both
- Boxed warning: increased suicidal thoughts and behaviour in children, teens and young adults under 25, especially early in treatment and after dose changes.
- Serotonin syndrome with other serotonergic drugs: triptans, tramadol, other antidepressants, lithium, St John’s wort, linezolid.
- Bleeding risk with NSAIDs, aspirin and blood thinners.
- Mania in people with undiagnosed bipolar disorder.
- Low sodium, especially in older adults.
- Angle-closure glaucoma in susceptible people.
Drug interactions
- Fluoxetine is a strong CYP2D6 inhibitor. It raises levels of many drugs, including some beta-blockers (metoprolol), tricyclic antidepressants, antipsychotics (risperidone, aripiprazole), atomoxetine, and codeine and tramadol, which it also makes less effective as painkillers. It reduces tamoxifen’s activation and is generally avoided in women taking tamoxifen.
- Duloxetine is a moderate CYP2D6 inhibitor and is broken down by CYP1A2. Strong CYP1A2 inhibitors such as fluvoxamine and ciprofloxacin raise duloxetine levels substantially and should be avoided. Smoking lowers duloxetine levels by about a third.
- Thioridazine and pimozide: contraindicated with fluoxetine, because of heart rhythm risks.
- Both: MAOIs are contraindicated.
Our SSRI comparison tool shows how fluoxetine’s interaction profile compares with other SSRIs.
What to expect in the first weeks
Side effects usually come before benefits with both drugs. Nausea, mild headache, sleep changes and jitteriness are most common in the first one to two weeks and often fade. Taking Cymbalta with food reduces its nausea. Taking Prozac in the morning reduces insomnia. Energy and sleep often improve before mood. Meaningful improvement in depression or anxiety usually shows at 2 to 4 weeks, with fuller effect by 6 to 8 weeks. For pain conditions, Cymbalta’s pain relief can appear within the first week or two, sometimes faster than its mood effects. Prozac’s long half-life means it takes about 4 to 5 weeks to reach steady levels, so a dose change takes longer to show its full effect than with Cymbalta.
Coming off Cymbalta safely
Because Cymbalta’s discontinuation symptoms can be strong, a planned taper matters. The label recommends a gradual dose reduction rather than stopping suddenly. In practice:
- Reduce in steps (for example 60 mg to 30 mg, then 20 mg) over at least 2 weeks, and longer after long-term use.
- If symptoms are hard to tolerate, go back to the previous dose and taper more slowly. Some people need very gradual reductions over months.
- Expect possible dizziness, “brain zaps”, nausea, irritability, vivid dreams and flu-like feelings. These are withdrawal effects, not necessarily a return of depression, though both can happen.
- Ask about a fluoxetine bridge if repeated tapers fail.
Older adults
In people over 65, both drugs raise the risk of low sodium (hyponatremia), falls and bleeding, especially with diuretics or blood thinners. Cymbalta’s label suggests starting at 30 mg in older adults with anxiety. Its effect on blood pressure and urinary hesitancy matters more in this group, as does its interaction with ciprofloxacin, a common antibiotic in older adults. Fluoxetine’s long half-life means side effects take a long time to clear, and its many interactions are a concern for people on several heart or psychiatric medicines. Neither is a clear winner for older adults. Shorter-acting SSRIs such as sertraline or escitalopram are often chosen first.
Pregnancy and breastfeeding
Both have pregnancy data. Fluoxetine has more, from decades of use. Late-pregnancy SSRI and SNRI exposure is linked to temporary newborn adaptation symptoms and a small increased risk of persistent pulmonary hypertension of the newborn. SNRIs near delivery have also been linked to a small increase in postpartum bleeding. For breastfeeding, fluoxetine’s long-lasting metabolite can build up in infants, so sertraline or paroxetine is often preferred. Duloxetine passes into milk in small amounts. Untreated depression carries real risks too, so decisions should be individual.
Cost and forms
Both are available as inexpensive generics. Fluoxetine comes in more forms (capsules, tablets, liquid, and a 90 mg weekly capsule for maintenance), which helps with children, swallowing difficulties and dose fine-tuning. Duloxetine comes only as delayed-release capsules (20, 30, 40 and 60 mg), which are designed to be swallowed whole. Ask a pharmacist before opening them, because the coated pellets protect the drug from stomach acid.
Who each one might suit
| Situation | Often favours |
|---|---|
| Depression or anxiety with chronic pain, nerve pain or fibromyalgia | Cymbalta |
| OCD, bulimia or panic disorder | Prozac |
| Child or teen with depression or OCD | Prozac |
| Tends to miss doses, or worried about withdrawal | Prozac |
| Regular heavy drinking or liver disease | Prozac (avoid Cymbalta) |
| Uncontrolled high blood pressure | Prozac |
| Takes many other medicines (heart, psychiatric, pain) | Often Cymbalta (fewer strong interactions than fluoxetine), but check individually |
| Taking tamoxifen | Avoid Prozac |
| Low energy and oversleeping with depression | Prozac’s activating effect may help |
Related comparisons: Cymbalta vs Lexapro, Cymbalta vs Celexa and Prozac vs Zoloft.
Frequently asked questions
Can you take Cymbalta and Prozac together?
Generally not, except briefly while switching under supervision. Fluoxetine raises duloxetine levels by blocking CYP2D6, both increase serotonin syndrome risk, and combining them hasn’t been shown to work better than one adequate antidepressant.
Is Cymbalta stronger than Prozac?
Not for depression on average. Both work about as well. Cymbalta adds proven pain relief for nerve pain, fibromyalgia and chronic musculoskeletal pain, while Prozac covers OCD, bulimia and panic disorder.
Which has worse withdrawal, Cymbalta or Prozac?
Cymbalta, by a wide margin. Its short half-life means levels drop quickly, causing dizziness, brain zaps, nausea and irritability if it’s stopped abruptly. Prozac’s very long half-life makes withdrawal uncommon and mild.
How do you switch from Cymbalta to Prozac?
Usually by tapering duloxetine while starting fluoxetine at a low dose. Fluoxetine’s long action can ease duloxetine withdrawal. The exact schedule should come from your prescriber.
Does Prozac help pain like Cymbalta?
Not as reliably. SSRIs have weaker and less consistent effects on chronic pain than SNRIs, and Prozac isn’t approved for any pain condition.
References
- Cymbalta (duloxetine) delayed-release capsules, prescribing information. Eli Lilly.
- Prozac (fluoxetine) prescribing information. Eli Lilly. DailyMed.
- Cipriani A, et al. Comparative efficacy and acceptability of 21 antidepressant drugs for the acute treatment of adults with major depressive disorder: a systematic review and network meta-analysis. Lancet. 2018;391:1357-1366.
- Skinner MH, et al. Duloxetine is both an inhibitor and a substrate of cytochrome P4502D6 in healthy volunteers. Clin Pharmacol Ther. 2003;73:170-177.
Try our interactive tool: SSRI comparison tool
Compare Zoloft, Lexapro, Prozac, Paxil and Celexa by approved uses, half-life and interactions.
About this article
Written by the Health Linear Editorial Team from primary sources such as FDA prescribing information, DailyMed, NIH and peer-reviewed studies, which are linked in the article. Last updated October 28, 2026.
Read our editorial process and medical disclaimer. Spotted an error? Tell us and we will correct it.