


EpiPen (epinephrine) and Benadryl (diphenhydramine) are sometimes confused as interchangeable allergy treatments, but they are not interchangeable for a severe reaction: EpiPen is the emergency treatment for anaphylaxis, and Benadryl is a supportive, secondary medication that should never replace it. This guide explains the critical difference and when each is appropriate.
This is general information, not medical advice, and is not a substitute for emergency medical care. If anaphylaxis is suspected, use epinephrine first and call emergency services immediately.
EpiPen vs Benadryl at a glance
| EpiPen (epinephrine) | Benadryl (diphenhydramine) | |
|---|---|---|
| Drug class | Adrenergic agonist (epinephrine) | First-generation antihistamine |
| Used for | Anaphylaxis (life-threatening allergic reaction) | Mild allergy symptoms, itching, hives |
| Speed of action | Seconds to minutes | 15-30 minutes minimum |
| Reverses airway swelling/low BP | Yes, directly | No |
| Appropriate as sole anaphylaxis treatment | Yes, it’s the first-line treatment | No, never as the primary treatment |
The single most important fact in this comparison
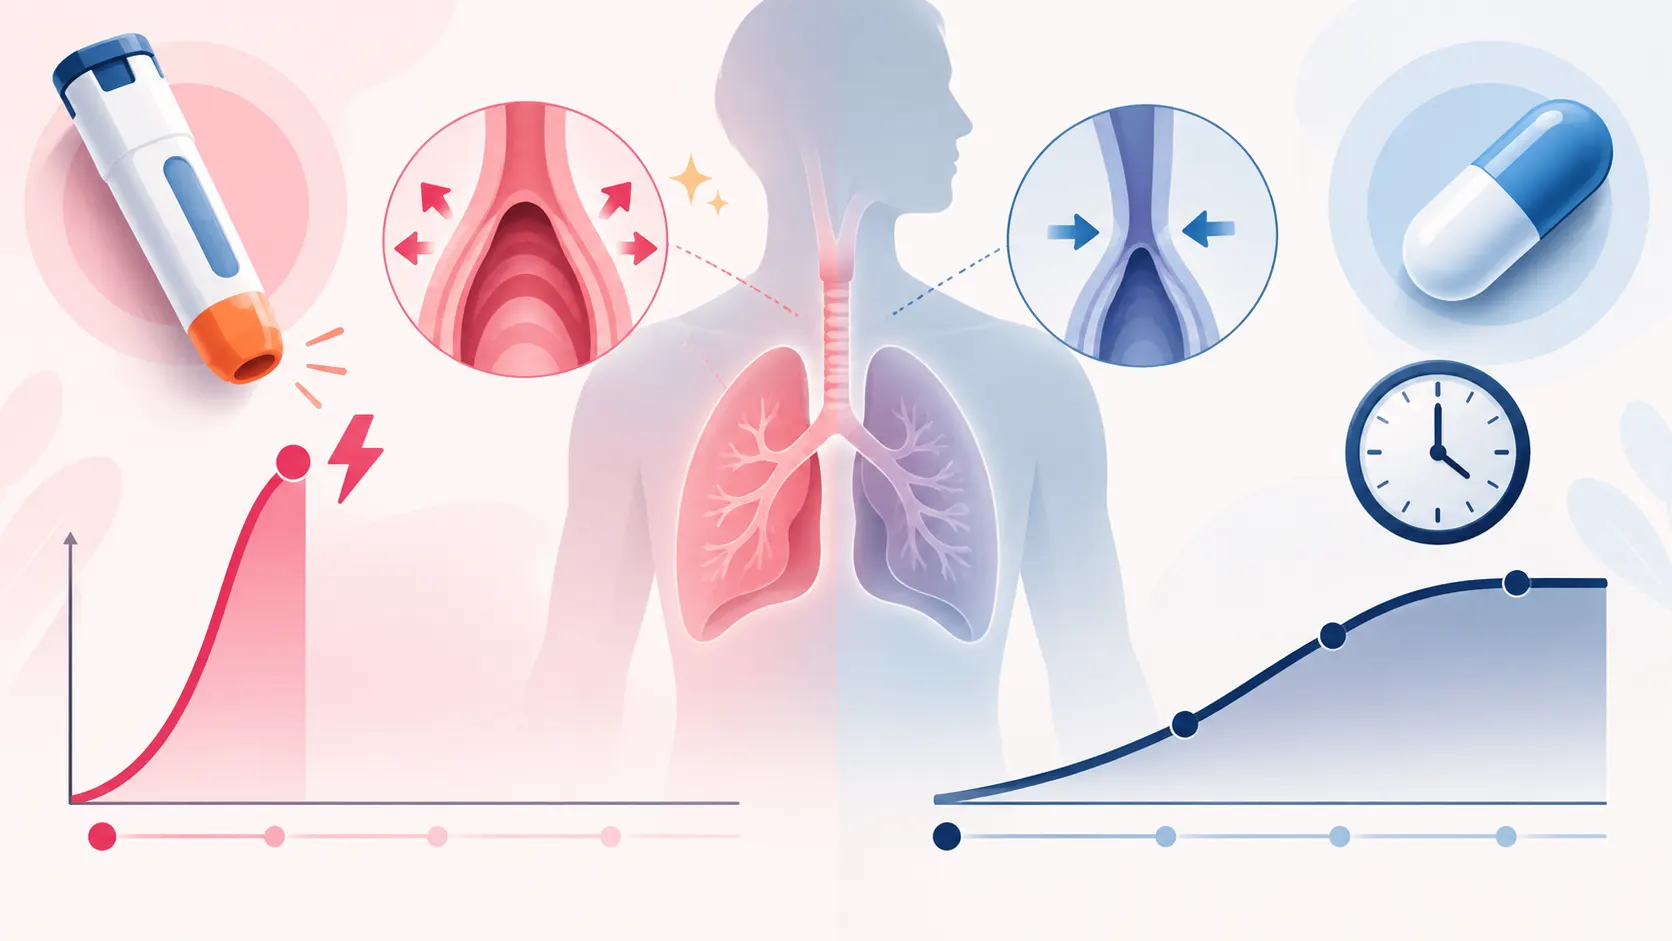
Benadryl does not treat anaphylaxis and should never be used as a substitute for epinephrine during a severe allergic reaction. Anaphylaxis is a life-threatening reaction that can involve airway swelling, a dangerous drop in blood pressure, and other rapidly progressing symptoms. Epinephrine (the drug in an EpiPen) works within seconds to minutes to constrict blood vessels, relax airway muscles, and reverse the dangerous physiological changes of anaphylaxis. Diphenhydramine, an antihistamine, works on a completely different and much slower timeline, and does not reverse the airway swelling or blood pressure drop that makes anaphylaxis dangerous. Waiting to see if Benadryl works before using an EpiPen during a true anaphylactic reaction can be fatal; if anaphylaxis is suspected, epinephrine should be given first, without delay, and emergency services called immediately afterward.
How each actually works
Epinephrine (adrenaline) is a naturally occurring hormone and neurotransmitter that, given as a medication via the EpiPen auto-injector, rapidly constricts blood vessels (raising blood pressure), relaxes the smooth muscle in airways (opening breathing passages), and reduces the release of additional inflammatory chemicals, directly counteracting the dangerous cascade of anaphylaxis at its physiological root.
Diphenhydramine is a first-generation antihistamine that blocks histamine receptors, reducing itching, hives, and mild swelling caused by histamine release. It’s useful for milder allergic symptoms but has no direct effect on blood pressure or airway muscle relaxation in the way epinephrine does, which is exactly why it cannot substitute for epinephrine in a true emergency.
When each is appropriate
Use an EpiPen (and call emergency services) for: any signs of anaphylaxis, including difficulty breathing, throat tightness or swelling, widespread hives combined with other symptoms, a sudden drop in blood pressure (dizziness, fainting), rapid heartbeat, or a known severe allergen exposure (certain foods, insect stings, medications) in someone with a prior severe reaction history.
Benadryl is appropriate for milder, localized allergy symptoms: seasonal allergy symptoms, mild hives without other systemic symptoms, or itching from a mild reaction, situations where there’s no indication of the more severe, whole-body reaction that defines anaphylaxis.
Can they be used together?
Yes, but with a specific order and understanding: current emergency guidance is that epinephrine should always be given first and without delay in suspected anaphylaxis; an antihistamine like Benadryl can be given as a secondary, supportive treatment for milder skin symptoms like itching or hives afterward, alongside continued monitoring and emergency medical follow-up, never as a first response or replacement.
Side effects
Epinephrine can cause a racing heart, anxiety, tremor, and elevated blood pressure, effects generally considered an acceptable tradeoff during a life-threatening emergency, and which typically resolve as the medication wears off.
Benadryl commonly causes drowsiness, dry mouth, and can impair coordination and alertness, side effects typical of first-generation antihistamines given their ability to cross into the brain more readily than second-generation options like Allegra or Claritin.
Frequently asked questions
Can Benadryl stop anaphylaxis?
No. Benadryl does not reverse the airway swelling or blood pressure drop that makes anaphylaxis dangerous. Epinephrine (EpiPen) is the required first-line treatment; Benadryl is never a substitute.
Should I give Benadryl before using an EpiPen if I’m not sure how severe the reaction is?
If anaphylaxis is suspected (breathing difficulty, throat swelling, widespread symptoms, or a known severe allergy history), use epinephrine first without delay, then call emergency services. Waiting to try Benadryl first in a true emergency can be dangerous.
Can I use both EpiPen and Benadryl?
Yes, epinephrine first for the emergency, with Benadryl potentially used afterward as supportive treatment for milder skin symptoms like itching, always with continued emergency medical follow-up.
How fast does an EpiPen work compared with Benadryl?
Epinephrine acts within seconds to minutes. Oral Benadryl typically takes at least 15 to 30 minutes to start working, far too slow to address a rapidly progressing anaphylactic reaction on its own.
What should I do after using an EpiPen?
Call emergency services immediately, even if symptoms improve, since anaphylaxis can recur (a “biphasic” reaction) and further medical monitoring and treatment are typically needed.
References
- General emergency medicine and allergy/immunology guidance on anaphylaxis management; consult FDA-approved epinephrine auto-injector labeling and an allergist for individualized emergency action plans.