


Hydroxocobalamin and cyanocobalamin are two forms of vitamin B12. Both treat B12 deficiency, but they differ in three ways.
- How long they stay in the body: after a 1,000 microgram injection, the body keeps about 30% of hydroxocobalamin but only about 15% of cyanocobalamin. Hydroxocobalamin injections can therefore be given every 2 to 3 months, against monthly for cyanocobalamin.
- Where they’re used: the UK and much of Europe use hydroxocobalamin as the standard injection, while the US mostly uses cyanocobalamin injections and tablets.
- Antidote use: only hydroxocobalamin, given in very high doses as Cyanokit, is used as an antidote for cyanide poisoning. And despite the name, the cyanide in cyanocobalamin is a tiny, harmless amount.
This is general information, not medical advice. B12 deficiency should be diagnosed and its cause found, because the cause decides the best form and route.
Hydroxocobalamin vs cyanocobalamin at a glance
| Hydroxocobalamin | Cyanocobalamin | |
|---|---|---|
| What it is | Natural form of B12 (made by bacteria), with a hydroxyl group attached to cobalt | Synthetic, very stable form, with a cyanide group attached to cobalt |
| Forms | Injection (intramuscular); high-dose IV Cyanokit | Injection, tablets, sublingual, nasal spray, most supplements and fortified foods |
| Retention after 1,000 mcg injection | About 30% | About 15% |
| Typical maintenance injection | 1 mg every 2 to 3 months (UK) | 1,000 mcg monthly (US and UK) |
| Cyanide poisoning antidote | Yes (Cyanokit, 5 g IV) | No |
| Main users | UK, Europe, Australia; emergency medicine everywhere | US standard; global supplements |
| Cost | Low (injections) | Very low |
Is cyanocobalamin the same as hydroxocobalamin?
They’re closely related but not identical. All forms of vitamin B12 share the same core: a large ring structure (a corrin ring) holding a cobalt atom. What differs is the small group attached to the cobalt:
- Cyanocobalamin: a cyanide (CN) group. It’s the most stable form, cheap to make, with a long shelf life, which is why it’s used in most tablets and fortified foods.
- Hydroxocobalamin: a hydroxyl (OH) group. This is what bacteria make naturally, and it binds more tightly to proteins in the blood.
- Methylcobalamin and adenosylcobalamin: the two “active” coenzyme forms that the body’s cells actually use.
Inside cells, cyanocobalamin and hydroxocobalamin are both converted into methylcobalamin and adenosylcobalamin. So for treating deficiency, they end up doing the same job. The differences are in how long they last and in a few special situations.
Cyanocobalamin vs cyanide: is it safe?
Yes. The cyanide group makes up only about 2% of the cyanocobalamin molecule by weight, so a 1,000 microgram dose contains roughly 20 micrograms of cyanide. That’s thousands of times less than a toxic amount. The body removes this small amount easily, using the same detox pathways that handle the trace cyanide found naturally in some plant foods and in tobacco smoke.
The one exception: in a rare inherited eye condition, Leber’s hereditary optic neuropathy, and in “tobacco amblyopia” (vision damage linked to smoking), the body’s cyanide handling may be impaired. In those cases hydroxocobalamin is used instead of cyanocobalamin.
Why hydroxocobalamin lasts longer
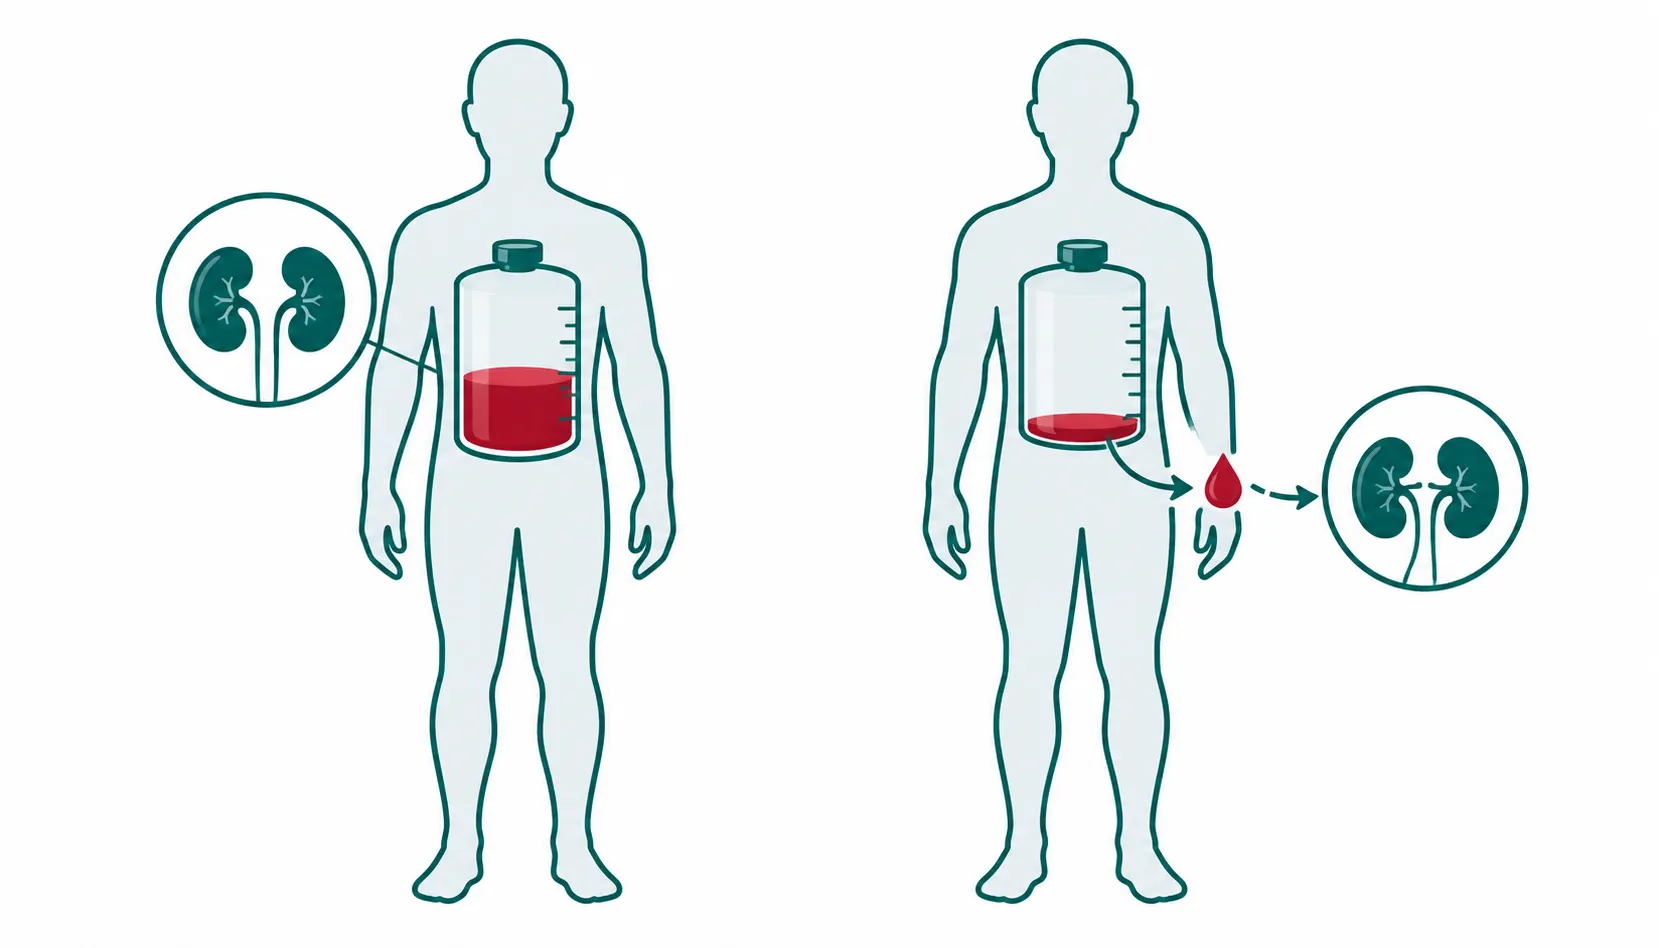
After a B12 injection, much of the dose is filtered out by the kidneys within a day. Hydroxocobalamin binds more strongly to transport proteins in the blood, so less is lost in the urine. UK product information reports that the body retains about 90% of a 100 microgram hydroxocobalamin dose and 30% of a 1,000 microgram dose. For cyanocobalamin, the figures are about 55% and 15%. Hydroxocobalamin also produces higher, longer-lasting blood levels from the same dose.
In practice, that’s the difference between injections every 2 to 3 months and monthly injections, which matters to someone who needs B12 shots for life.
Treating B12 deficiency: how each is used
| Situation | Hydroxocobalamin (UK BNF) | Cyanocobalamin (US and UK) |
|---|---|---|
| Pernicious anemia, no nerve symptoms | 1 mg IM three times a week for 2 weeks, then 1 mg every 2 to 3 months for life | US: commonly 1,000 mcg IM daily for a week, weekly for a month, then monthly for life. UK: 0.25 to 1 mg on alternate days for 1 to 2 weeks, then monthly |
| With nerve symptoms (numbness, balance or memory problems) | 1 mg on alternate days until no further improvement, then every 2 months | 1 mg on alternate days while improving, then monthly |
| Diet-related deficiency (e.g. vegan) | Twice-yearly 1 mg injection is an option | Oral 50 to 150 mcg daily (UK), or higher-dose supplements |
| Oral high-dose treatment | Not used by mouth | 1,000 to 2,000 mcg daily by mouth can match injections, even in many people with absorption problems |
Oral vs injection: a 2018 Cochrane review (Wang and colleagues) found that 1,000 micrograms of oral B12 daily raised blood levels about as well as injections over 3 to 4 months, and 2,000 micrograms daily did even better. About 1% of a large oral dose is absorbed passively without intrinsic factor, the stomach protein that’s missing in pernicious anemia. That’s enough at high doses. Injections are still preferred when there are neurological symptoms, severe deficiency, or doubts about taking tablets reliably.
Hydroxocobalamin as a cyanide antidote (Cyanokit)
This is where the two forms differ completely. Hydroxocobalamin’s hydroxyl group can swap with cyanide. Each molecule grabs one cyanide ion and turns into cyanocobalamin, which the kidneys then safely excrete. To neutralize a poisonous dose, enormous amounts are needed. Cyanokit is given as 5 grams by IV infusion over 15 minutes in adults (70 mg/kg in children), repeated once if needed. That’s about 5,000 times a typical B12 injection.
Cyanokit is used for suspected cyanide poisoning, most often in smoke inhalation from house fires (burning plastics release hydrogen cyanide), and in industrial or deliberate poisoning. Cyanocobalamin can’t do this job, because its cobalt is already bound to cyanide.
Effects specific to high-dose hydroxocobalamin:
- Red skin and red urine in almost everyone. The skin color fades over about 2 weeks, and urine color can last up to 5 weeks. It’s harmless but striking.
- A temporary rise in blood pressure.
- Interference with lab tests that use color (some liver and kidney tests, bilirubin, magnesium), and false “blood leak” alarms on dialysis machines. Hospitals are alerted when Cyanokit has been given.
- Rarely, allergic reactions or kidney injury from oxalate crystals.
What about methylcobalamin?
Methylcobalamin is one of the active coenzyme forms and is popular in supplements marketed as “natural” or “better absorbed”. The evidence doesn’t show it’s clinically better than cyanocobalamin for treating or preventing deficiency in most people. All forms are converted to the same active coenzymes inside cells. Methylcobalamin is less stable (light-sensitive) and usually more expensive. People with certain rare inherited B12 metabolism disorders are treated with specific forms, typically hydroxocobalamin injections, under specialist care. For everyone else, the dose, route and regularity matter more than the form.
Side effects
- Both (at normal doses): generally very well tolerated. Possible injection-site pain, mild diarrhea, itching or a feeling of swelling. Rarely, allergic reactions, including anaphylaxis with injections. Both contain cobalt, and 1 to 3% of people have a cobalt allergy.
- Low potassium in the first days: when severe deficiency anemia is treated, new red blood cells are made rapidly and pull potassium out of the blood. People with severe anemia are monitored early in treatment.
- Acne-like rash is occasionally reported with B12 injections.
- Red urine is specific to high-dose hydroxocobalamin, not standard B12 shots.
Who needs B12 treatment, and why the cause matters
- Pernicious anemia (autoimmune loss of intrinsic factor) needs lifelong treatment: injections, or high-dose oral therapy if suitable.
- Stomach or bowel surgery (gastric bypass, removal of the end of the small intestine) and conditions like Crohn’s disease reduce absorption.
- Medicines: long-term metformin and acid-reducing drugs (PPIs such as omeprazole, and H2 blockers) lower B12 absorption. People on these for years are worth testing.
- Vegan diets contain almost no natural B12, so supplements or fortified foods are essential.
- Older adults absorb B12 from food less well because of reduced stomach acid.
Untreated deficiency can cause anemia, fatigue, a sore tongue, numbness and tingling, balance problems, memory problems and mood changes. Nerve damage can become permanent if treatment is delayed. If you take acid reducers long term, our PPI comparison tool explains the main options, and our hydroxocobalamin guide covers deficiency symptoms in more detail.
How B12 deficiency is tested
Before choosing a form, the deficiency and its cause need confirming. Common tests:
- Serum B12: the first-line test. Low levels support deficiency, but “borderline” results are common and the test misses some true deficiencies.
- Methylmalonic acid (MMA) and homocysteine: these build up when cells lack B12, so raised levels confirm a functional deficiency when serum B12 is borderline. Homocysteine also rises with folate deficiency, while MMA is more specific to B12.
- Active B12 (holotranscobalamin): measures the fraction of B12 available to cells. Used in some labs.
- Full blood count: large red blood cells (macrocytosis) and anemia are classic signs, but nerve damage can occur with a normal blood count.
- Intrinsic factor antibodies: positive results confirm pernicious anemia, which means lifelong treatment.
Testing should be done before starting supplements where possible, because even a few days of B12 can normalize blood levels and mask the diagnosis.
Other ways to take B12: sublingual, nasal and subcutaneous
- Sublingual tablets and lozenges (usually cyanocobalamin or methylcobalamin) are dissolved under the tongue. Studies show they work about as well as swallowed tablets of the same dose. Most of the B12 is still swallowed and absorbed in the gut.
- Nasal spray (cyanocobalamin, sold as Nascobal in the US) is a prescription option for maintenance after levels are corrected. It’s given once weekly and avoids needles, but costs more.
- Subcutaneous injection (under the skin rather than into muscle) is used in some practices, particularly for people on blood thinners. Many patients learn to self-inject cyanocobalamin at home.
Pregnancy, breastfeeding and children
B12 needs rise in pregnancy and breastfeeding, and deficiency in the mother can cause deficiency in a breastfed baby, which can show as poor feeding, failure to thrive, low muscle tone and developmental delay. This is a particular risk for vegan mothers who don’t supplement. Both cyanocobalamin and hydroxocobalamin are safe to use in pregnancy and breastfeeding at treatment doses. Children with deficiency are treated with weight-adjusted doses under specialist guidance. Hydroxocobalamin is often used for infants with inherited B12 disorders.
Can you take too much B12?
B12 has no established upper intake limit, because excess is excreted in urine and toxicity from normal supplements hasn’t been shown. That said, very high blood B12 levels in someone who isn’t taking supplements can be a sign of liver disease or certain blood disorders and should be checked. High-dose supplements also make B12 blood tests hard to interpret, so tell your clinician if you take them before any B12 testing. People with kidney disease should discuss long-term high doses of cyanocobalamin with their doctor, because cyanide clearance depends partly on the kidneys.
Practical tips for B12 injections
- Keep a written record of injection dates. Missed maintenance doses in pernicious anemia can slowly bring back symptoms over months.
- Symptoms such as tiredness often improve within days to weeks of starting treatment. Nerve symptoms take longer, often months, and may not fully recover if they were long-standing.
- Some people feel symptoms returning before their next injection is due. Talk to your clinician. UK guidance allows shorter intervals for people with neurological involvement.
- Folate deficiency often coexists with B12 deficiency. Folate alone should not be given to someone who is B12-deficient, because it can correct the anemia while nerve damage progresses.
Which one is better?
| Situation | Usually preferred |
|---|---|
| Lifelong injections, fewer shots wanted | Hydroxocobalamin (every 2 to 3 months) |
| US patient getting monthly shots | Cyanocobalamin (standard and widely covered) |
| Taking B12 by mouth | Cyanocobalamin (stable, cheap, well studied) |
| Leber’s hereditary optic neuropathy or tobacco amblyopia | Hydroxocobalamin |
| Cyanide poisoning or smoke inhalation | Hydroxocobalamin (Cyanokit) only |
| Rare inherited B12 metabolism disorders | Hydroxocobalamin, under specialist care |
Frequently asked questions
Is hydroxocobalamin better than cyanocobalamin?
For injections, hydroxocobalamin is retained better, so it can be given every 2 to 3 months instead of monthly. For tablets, cyanocobalamin is the standard and works well. Both correct deficiency.
Does cyanocobalamin contain cyanide?
Yes, a tiny amount, about 20 micrograms in a 1,000 microgram dose. That’s far below a harmful level and easily removed by the body.
Why is hydroxocobalamin used for cyanide poisoning?
Its hydroxyl group swaps with cyanide, forming harmless cyanocobalamin that the kidneys excrete. Very high IV doses (5 g as Cyanokit) are needed.
Is methylcobalamin better than cyanocobalamin?
There’s no good evidence that it is for most people. All forms are converted to the same active coenzymes in cells. Cyanocobalamin is more stable and cheaper.
Can I switch from cyanocobalamin to hydroxocobalamin injections?
Yes. It’s common when moving between countries or to reduce how often you need injections. Your prescriber will set the new schedule, typically 1 mg every 2 to 3 months for hydroxocobalamin.
References
- Hydroxocobalamin. British National Formulary (BNF). NICE.
- Cyanocobalamin. British National Formulary (BNF). NICE.
- Wang H, et al. Oral vitamin B12 versus intramuscular vitamin B12 for vitamin B12 deficiency. Cochrane Database Syst Rev. 2018.
- NICE Clinical Knowledge Summaries. Anaemia: B12 and folate deficiency, management.
- Cyanokit (hydroxocobalamin for injection) prescribing information. DailyMed.
- Cyanocobalamin. StatPearls. NCBI Bookshelf.
- Hydroxocobalamin medical countermeasure. CHEMM, US Department of Health and Human Services.
About this article
Written by the Health Linear Editorial Team from primary sources such as FDA prescribing information, DailyMed, NIH and peer-reviewed studies, which are linked in the article. Last updated October 28, 2026.
Read our editorial process and medical disclaimer. Spotted an error? Tell us and we will correct it.
Which b12 is most effective in Melanin People.